Diagnostic medical devices in 2026 and the changes shaping testing
Why diagnostic medical devices matter in 2026
Diagnostic medical devices are no longer limited to laboratory analyzers and imaging scanners. The category now covers in vitro diagnostic tests, diagnostic ultrasound and x-ray systems, connected monitoring tools, accessories and software used for screening, triage or clinical interpretation. As of October 31, 2026, the main change is not one breakthrough product. It is the combined effect of risk-based regulation, AI-enabled workflows, tighter quality expectations, cybersecurity obligations and pressure to improve access.
For hospitals, laboratories and distributors, the practical question is straightforward: can the device produce reliable diagnostic information in its intended setting, with documented regulatory status, validated performance, maintainable infrastructure and post-market support?

For more coverage of testing, imaging and device policy, visit the Diagnostic Devices section.
What counts as a diagnostic medical device
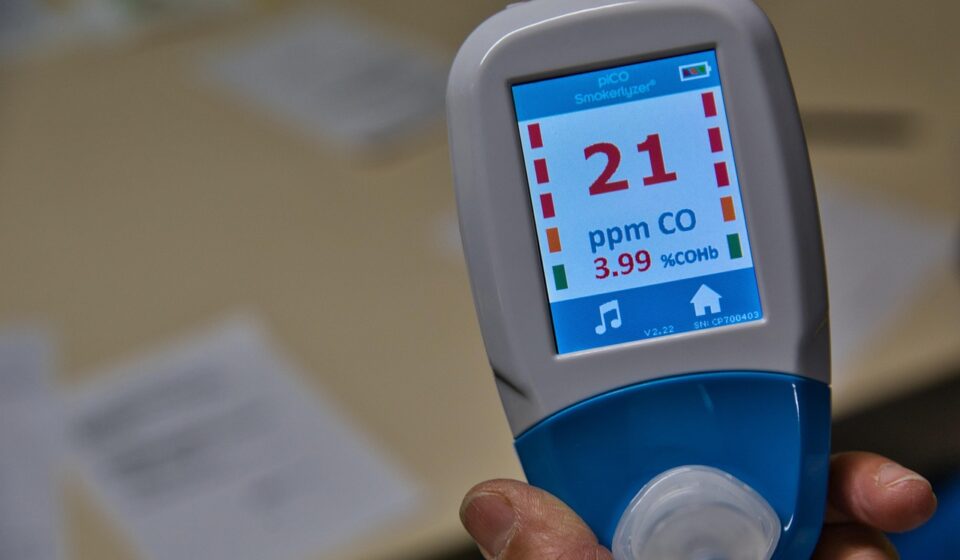
A diagnostic medical device is generally a medical device intended to help identify, screen for, monitor or provide information about a disease, condition or physiological state. The diagnostic function may come from hardware, reagents, instruments, software or a combination of these elements. Intended use matters more than the product’s appearance. A handheld reader, a laboratory assay, a CT scanner and a software algorithm may all fall within diagnostic device oversight if their claims support medical decision-making.
- In vitro diagnostics examine specimens taken from the human body, such as blood, tissue, urine or swabs. They may include reagents, test kits, instruments, calibrators, controls and related software.
- Diagnostic imaging devices include x-ray, CT, MRI, ultrasound, mammography, nuclear medicine and image-processing systems used to visualize anatomy or physiology.
- Monitoring and measurement devices generate diagnostic or clinical status information, such as glucose meters, ECG systems, oximeters and certain patient monitoring platforms.
- Software as a medical device can perform a medical purpose without being part of a dedicated hardware device, for example image triage, quantitative analysis or risk scoring software.
The boundary is not always obvious. A general wellness app may not be regulated as a medical device, while a similar app that claims to detect arrhythmia, classify lesions or guide treatment could trigger medical device requirements. Manufacturers and buyers therefore need to start with intended use, indications for use, labeling, claims and the clinical context in which results will be interpreted.
Regulatory status is becoming a practical purchasing question
Regulatory classification is not only a manufacturer issue. It affects procurement, clinical implementation, reimbursement planning, risk management and liability. In the United States, FDA materials describe a risk-based system with Class I, Class II and Class III devices. Regulatory controls increase as risk increases. Many Class II devices require 510(k) clearance, while most Class III devices require premarket approval. The FDA also notes that it has classifications for approximately 1,700 generic device types grouped into 16 medical specialty panels.
For diagnostic medical devices, buyers should verify more than the brand name. The key questions are whether the product is cleared, approved, De Novo authorized, exempt or outside a specific premarket pathway; whether that status matches the marketed claims; and whether the device is being used within its intended population, specimen type and setting. A cleared device used in a different clinical workflow may still require local validation or risk assessment.
The laboratory-developed test debate shows why current status matters. On May 6, 2024, the FDA issued a final rule that would have changed oversight of many laboratory-developed tests. A federal district court vacated that rule on March 31, 2025, and on September 19, 2025, the FDA issued a final rule reverting the relevant regulatory text to its prior wording. Any diagnostic strategy that still relies on the 2024 phaseout timetable should be updated.
In Europe, the In Vitro Diagnostic Regulation continues to shape portfolios and supply planning. Regulation (EU) 2024/1860 further extended certain IVDR transition periods for qualifying legacy IVDs, with timing dependent on risk class and conditions such as no significant design or intended-purpose changes, quality system requirements and timely notified body applications. New devices and certain lower-risk non-sterile class A legacy devices have had to comply with the IVDR since May 2022.
AI and software are changing diagnostic workflows
AI-enabled diagnostic tools are moving from experimental demonstrations into regulated workflows, especially in radiology, cardiology, pathology, gastroenterology and neurology. FDA’s AI-enabled medical device list includes devices authorized for marketing in the United States and shows many 2026 entries in radiology, including segmentation, ultrasound, mammography and image-analysis tools. The list is intended to improve transparency, but the FDA also states that it is not a complete catalog of every AI-enabled device.
The important point is that AI does not remove the need for evidence. A diagnostic algorithm still needs a defined intended use, training and validation methods appropriate to that use, performance metrics that match clinical risk, human factors evaluation and post-market monitoring. For adaptive or frequently updated software, change management is especially important. FDA guidance on predetermined change control plans for AI-enabled device software functions describes how certain planned modifications can be prospectively specified and authorized, rather than handled as unexpected changes after deployment.
Healthcare organizations should avoid treating AI as a stand-alone answer. A more useful evaluation is whether the tool improves a defined workflow, whether it was tested on relevant patient populations, whether users understand its limitations and whether the institution can monitor false positives, false negatives, drift, downtime and cybersecurity events after adoption.
Quality systems and cybersecurity are now part of diagnostic performance
Analytical accuracy is only one part of diagnostic reliability. The same test or imaging system can perform differently when manufacturing controls, calibration, software updates, consumables, training and maintenance are weak. That is why quality management has become a more visible purchasing and compliance factor.
In the United States, the FDA Quality Management System Regulation became effective on February 2, 2026. The rule amends device current good manufacturing practice requirements in 21 CFR Part 820 by incorporating ISO 13485:2016, with FDA-specific requirements still controlling where applicable. For diagnostic device stakeholders, the practical effect is closer alignment between U.S. quality system expectations and international medical device quality management practices. See also: clinical equipment.
Cybersecurity also belongs in diagnostic evaluation because connected devices can affect patient safety and data integrity. Diagnostic workstations, cloud-connected analyzers, imaging systems and AI platforms may depend on networks, user credentials, remote service access and software updates. FDA cybersecurity guidance finalized in 2025 emphasizes secure development and premarket information for cyber devices. Buyers should ask about software bills of materials, vulnerability disclosure, update mechanisms, access controls, encryption, backup procedures and the expected support period.
Quality and cybersecurity questions should be addressed before installation, not after the first incident. A strong procurement file should include regulatory evidence, performance evidence, installation requirements, service commitments, training plans, data governance responsibilities and escalation pathways for safety or security problems.
Access and procurement are moving beyond price
WHO describes medical devices as essential to prevention, diagnosis, treatment, rehabilitation and emergency response, with an estimated 2 million kinds of medical devices on the global market. The access challenge is not only whether a device exists. It is whether the device can be selected, financed, installed, maintained and used correctly in the intended setting.
For diagnostic devices, procurement failures often come from overlooked operating requirements. A low purchase price may not include reagents, calibration materials, probes, quality controls, software licenses, cybersecurity updates, replacement parts, service visits, staff training or compatible infrastructure. Imaging equipment may require shielding, stable power, cooling, specialist operators and preventive maintenance. Molecular diagnostics may require biosafety procedures, temperature-controlled logistics and contamination controls.
WHO’s MeDevIS platform, announced in July 2024, reflects a broader move toward structured device information for selection, procurement and use. Its value for buyers is the same principle that should guide every diagnostic purchase: name the device correctly, match it to the level of care, understand infrastructure requirements and connect the product choice to clinical guidelines and patient needs.
A practical evaluation checklist for diagnostic medical devices
| Evaluation area | What to verify | Why it matters |
|---|---|---|
| Intended use | Indications, population, specimen type or imaging application | Defines whether the device fits the clinical workflow |
| Regulatory status | Clearance, approval, authorization, exemption or CE conformity pathway | Prevents reliance on unsupported marketing claims |
| Performance evidence | Analytical validity, clinical validity, sensitivity, specificity and limitations | Shows whether the result can support decisions |
| Quality system | ISO 13485 alignment, design controls, risk management and complaint handling | Supports consistent manufacturing and lifecycle control |
| Software and cybersecurity | Update policy, access control, vulnerability response and data protection | Reduces safety, privacy and operational risks |
| Total cost of ownership | Consumables, service, calibration, licenses, staffing and downtime | Prevents underestimating long-term budget impact |
Frequently asked questions
What is the difference between diagnostic medical devices and IVDs?
IVDs are a subset of diagnostic medical devices. They test specimens taken from the human body, such as blood or tissue. Diagnostic medical devices also include imaging systems, monitoring devices and software that generate diagnostic information without necessarily testing a specimen.
Does FDA clearance mean a diagnostic device is right for every hospital?
No. Clearance or authorization supports legal marketing for a defined intended use, but hospitals still need to confirm workflow fit, user training, patient population, local validation needs, cybersecurity requirements, service coverage and integration with existing systems.
Are AI diagnostic devices regulated like other medical devices?
When AI software has a medical purpose and meets the definition of a device, it is subject to medical device oversight. The evidence must address the claimed use, data quality, validation, human interaction, risks from incorrect outputs and post-market monitoring.
What changed for U.S. device quality systems in 2026?
The FDA Quality Management System Regulation became effective on February 2, 2026. It incorporates ISO 13485:2016 into the U.S. device quality system framework while retaining FDA-specific legal requirements where they apply.
Why do EU IVDR transition dates matter outside Europe?
Many diagnostic manufacturers sell globally. IVDR transition planning can affect product availability, documentation, notified body capacity, labeling and portfolio decisions. Buyers outside Europe may still feel the impact if a supplier changes or discontinues a diagnostic product.


